
At Sofusa, we asked:
“Why are we delivering biologic immune treatments into the blood, “when the drug targets live in the lymphatics?”
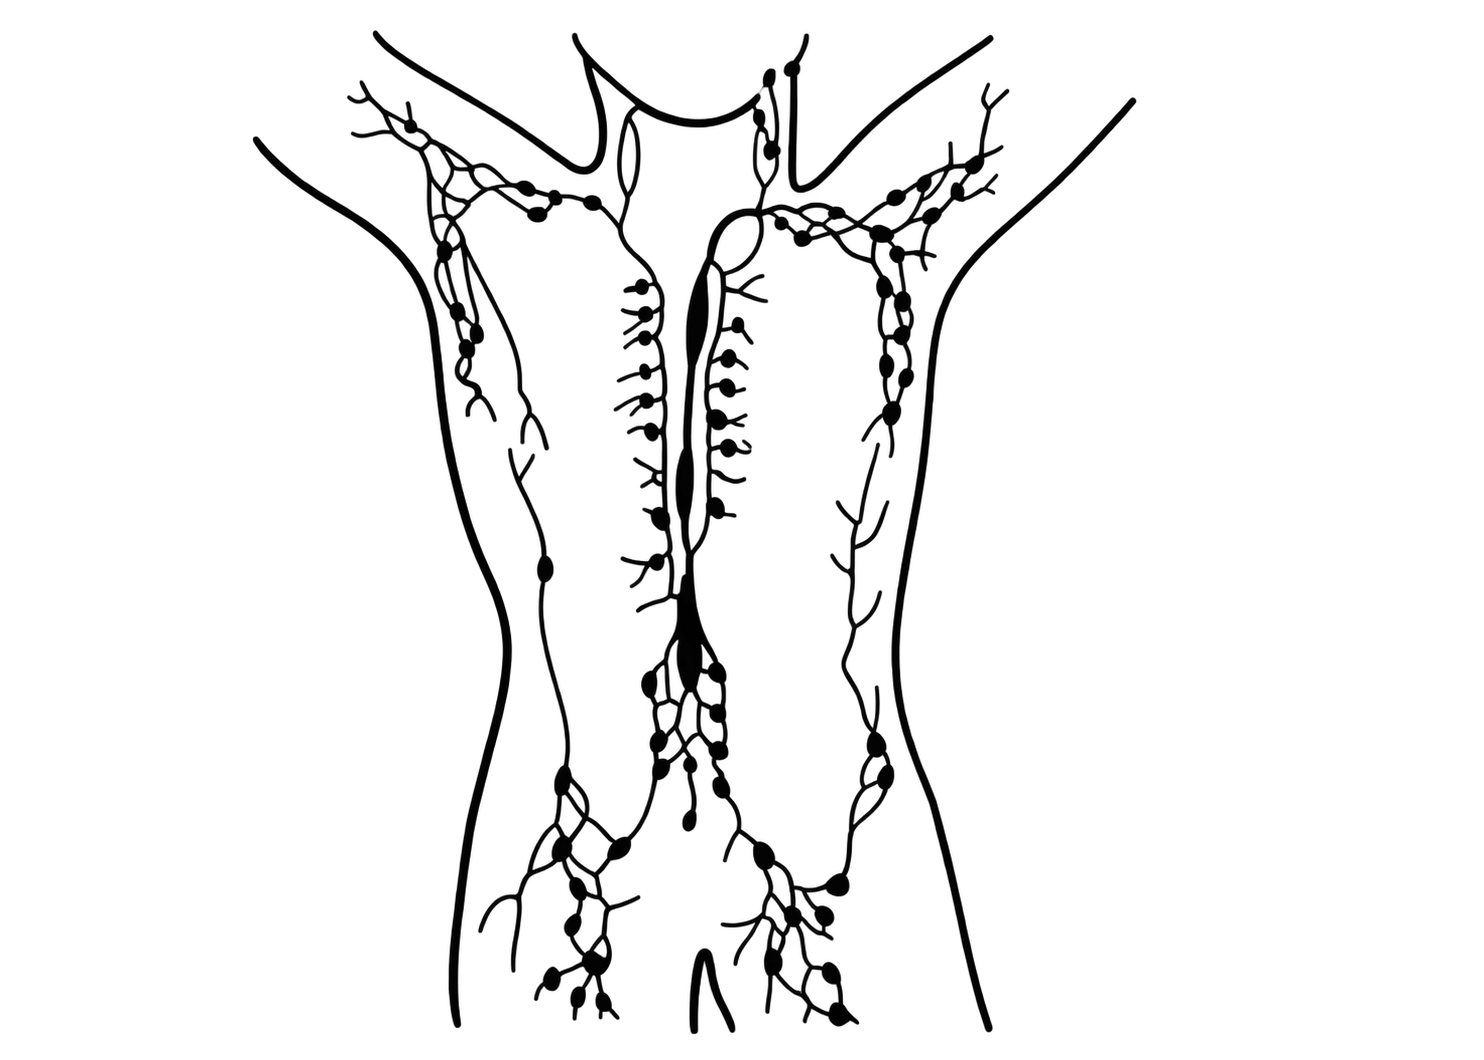
Empower the Lymphatics.
Transform Biologic Therapy.
Systemic IV and subcutaneous bolus injections flood the blood vasculature, diluting large-molecule therapeutics and often increasing systemic toxicity before drugs reach immune targets.
SOFUSA accesses dermal lymphatic capillaries just beneath the epidermis to deliver continuous, targeted biologic therapies directly into lymphatic capillaries and to tumor draining lymph nodes.
More immunotherapy reaches targets in the lymphatics prior to entering the bloodstream.
Direct Connection to the Body’s Immune Superhighway
Making Remission Possible Again in Refractory RA
Giving Hope to Patients Not Responding to Traditional Injections
“In a Phase 1b trial (NCT04559412), 10/10 refractory RA patients failing standard subcutaneous etanercept achieved significant clinical improvement at half the dose while tripling lymphatic pump rates.”
Five IND’s,
Three Sponsored Studies,
Two Investigator Initiated Studies
| Title | Biologic Treatment | IND Status | Key Clinical Observations |
|---|---|---|---|
| Refractory Rheumatoid Arthritis (RA) | Enbrel® (etanercept / Anti-TNFα) | Cleared IND Phase 1b completed (NCT04559412) | 10 of 10 patients with moderate to severe RA and not improving for at least 3 months saw a meaningful clinical improvement across disease measures at 50% of the subcutaneous dose. |
| Cutaneous T-Cell Lymphoma (CTCL) | Keytruda® (pembrolizumab / Anti-PD-1) | Cleared IND Phase 1b completed (NCT04118868) | Direct tumor-draining lymph nodes treatment resulted in 67% patients achieving partial or complete response |
| Advanced Metastatic Melanoma | Opdivo® + Yervoy® (nivolumab + ipilimumab) | Cleared IND Phase 1 IIT (Mayo Clinic, NCT04967196) | Safety study of intralymphatic delivery of a full dose of ipilimumab via SOFUSA DoseConnect™ resulted in zero device-related dose limiting toxicities. |
| In-Transit Melanoma | Danburstotug (STI-3031 / Anti-PD-L1) | Cleared IND Phase 1 IIT (Mayo Clinic, NCT05393713) | Intra-lymphatic micro-infusion at 25% of standard cycle dose to target metastases along lymphatic channels (Study not initiated). |
| PK Study in Healthy Volunteers | Sumatriptan | Cleared IND Phase 1 PK Study (NCT03229898) | Demonstrated PK tuning and bioavailability comparable to subcutaneous injections |
Figures from Sofusa / Sorrento Therapeutics disclosures and peer-reviewed literature (Arthritis Res. Ther. 2017; PMC6857054). Preclinical metrics are from biodistribution models and are not equivalent to human efficacy.
Sofusa Holdings is building the future of precision lymphatic medicine.
By enabling clinicians to both visualize and treat the lymphatic system, we aim to reveal biology, improve therapeutic precision, and transform the treatment of immune-mediated diseases.